DR. ASHOK KUMAR GI Surgeon & Oncologist • Ex-Prof. SGPGIMS Consult
Clinical Registry & Media Press Audits

Documented Surgical Cases & Operative Milestones.

Clinical portfolio featuring press clippings, oncological resections, and complex reconstructions performed by Dr. Ashok Kumar across SGPGIMS, KGMU, SNMC, RMLIMS, and Lapetos Healthcare.

Case 01 Diaphragm, Spleen, Kidney

Single-Stage Laparoscopic Multi-Organ Reduction and Diaphragmatic Hernia Repair

Presentation: 19-year-old male with persistent severe upper abdominal pain, postprandial vomiting, and acute exertional dyspnea.

Diagnosis: Massive diaphragmatic hernia with intrathoracic herniation of stomach, spleen, and left kidney, causing left lung compression atelectasis.

Procedure: Laparoscopic reduction of herniated viscera; splenectomy for hilar torsion and hemorrhagic congestion; retroperitoneal repositioning of kidney and stomach; tension-free primary closure with composite mesh reinforcement.

Outcome: 7-hour operative duration. Oral liquids initiated on POD 2; discharged stable on Post-Operative Day 3.


Newspaper report on laparoscopic diaphragmatic hernia surgery with multi-organ reduction by Dr. Ashok Kumar at SGPGI Lucknow
Press Coverage: SGPGI Diaphragmatic Hernia Multi-Organ Repair
Case 02 Abdominal Wall & Stomach

Synchronous Bariatric Surgery and Complex Incisional Hernioplasty

Presentation: Class III morbid obesity (weight up to 135 kg; BMI > 40–50 kg/m²), severe metabolic comorbidities (T2D, hypertension, sleep apnea), and massive incisional hernias.

Clinical Challenge: High failure rates for isolated hernia repairs in high-BMI patients due to elevated intra-abdominal pressure.

Procedure: Single-stage combined laparoscopic bariatric surgery with comprehensive adhesiolysis, defect closure, and sublay/intraperitoneal onlay prosthetic mesh repair.

Outcome: Excess weight loss of 11–28 kg documented over follow-up, durable abdominal wall repair, and significant glycemic improvement.

Press media clipping on synchronous bariatric surgery and complex incisional hernia repair by Dr. Ashok Kumar at SGPGI Lucknow
Press Coverage: SGPGI Bariatric Metabolic & Hernioplasty Series
Case 03 Gallbladder & Segments IVb/V

Laparoscopic Extended Cholecystectomy with Wedge Hepatectomy

Presentation: 42-year-old female with Class II obesity (92 kg) presenting with right upper quadrant pain and early-stage gallbladder carcinoma.

Minimally Invasive Procedure: Radical laparoscopic extended cholecystectomy; 3 cm en-bloc wedge resection of the adjacent liver bed (Segments IVb/V) via harmonic scalpel; systematic hepatoduodenal ligament lymphadenectomy.

Outcome: Minimal blood loss, zero wound breakdown or pulmonary compromise compared to open laparotomy; discharged on POD 5.

Newspaper coverage of breakthrough laparoscopic gallbladder cancer surgery and wedge liver resection by Dr. Ashok Kumar
Press Coverage: SGPGI Laparoscopic Gallbladder Cancer Resection
Case 04 Spleen & Peritoneal Cavity

Open Resection of Giant Splenomegaly (8 kg Splenectomy)

Presentation: 35-year-old male with massive abdominal distension over 3 years, chronic severe anemia, and secondary dyspnea.

Diagnostic Workup: Spleen occupying the entire left hemiabdomen and extending into the pelvis, causing severe contralateral vascular displacement.

Intervention: Open laparotomy with coordinated massive transfusion (70 units perioperatively); sequential ligation of massive hilar collateral plexuses; intact resection of 8 kg spleen.

Outcome: ICU monitoring for 48 hours; complete hematologic stabilization and preserved renal function.

Media press article documenting life-saving 8 kg giant splenectomy surgery by Dr. Ashok Kumar at SN Medical College Agra
Press Coverage: SNMC Agra 8 kg Giant Splenic Resection
Case 05 Hypopharynx / Upper Esophagus

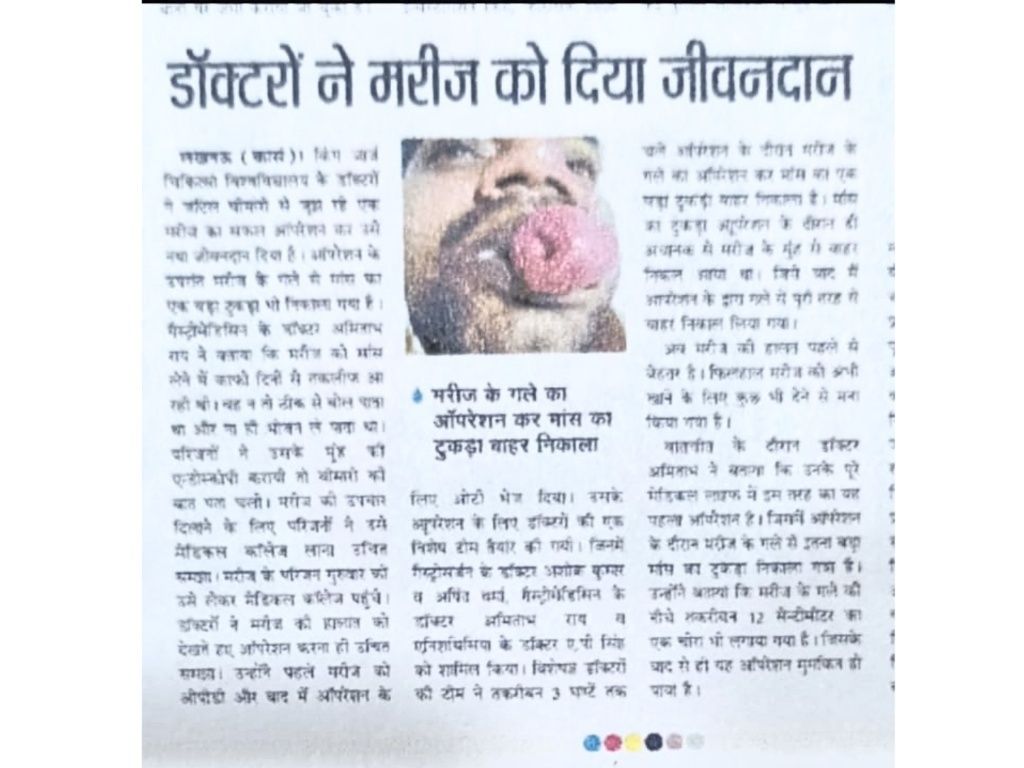
Emergent Transcervical Excision of Prolapsing Pharyngeal Mass

Presentation: Adult male with severe high dysphagia presenting with acute airway obstruction triggered by spontaneous intraoral prolapse of a large fleshy cervical mass during retching.

Protocol: Emergent intervention under general anesthesia with difficult-airway precautions; targeted anterior cervical exploration; base pedicle ligation and total excision.

Outcome: Immediate relief of laryngeal obstruction; complete restoration of mucosal integrity and normal swallowing.

Newspaper clipping covering emergency upper GI tumor excision and airway salvage by Dr. Ashok Kumar at KGMU Lucknow
Press Coverage: KGMU Emergency Obstructing Pharyngeal Mass Excision
Case 06 Esophagus & Mediastinum

Transhiatal Esophagectomy (THE) without Thoracotomy

Presentation: 65-year-old female with progressive dysphagia and weight loss diagnosed with mid-to-distal esophageal squamous cell carcinoma.

Surgical Approach: Transhiatal esophageal mobilization through combined abdominal and left cervical incisions, sparing thoracotomy; tubularized gastric pull-up transposition and cervical esophagogastrostomy.

Outcome: Sparing of chest wall mechanics eliminated pulmonary complications; negative R0 margins; oral diet resumed on POD 10.

Press article chronicling transhiatal esophagectomy without thoracotomy for foodpipe cancer by Dr. Ashok Kumar at SN Medical College
Press Coverage: SNMC Transhiatal Esophagectomy Sparing Thoracotomy
Case 07 Pylorus & Anal Sphincter

Autologous Pyloric Valve Transposition (Neosphincter) for Faecal Incontinence

Indication: End-stage faecal incontinence refractory to primary repair, facing permanent diverting stoma.

Physiological Innovation: Harvest of autologous vascularized gastroduodenal pyloric sphincter; pedicled transposition into the perineum encircling the anal canal to act as an autologous neosphincter.

Outcome: Transposed pyloric muscle maintained baseline tonic closure (2–3 hours), successfully restoring dynamic biological continence and avoiding a permanent colostomy.

Newspaper report on pioneering autologous pyloric valve transposition neosphincter surgery by Dr. Ashok Kumar at KGMU and RMLIMS
Press Coverage: KGMU/RMLIMS Pyloric Valve Biological Neosphincter
Case 08 Spleen & Splenic Hilum

Radical Resection of a 6 kg Splenic Neoplasm

Presentation: 56-year-old male with long-standing massive abdominal distension, severe early satiety, and cytopenias requiring transfusion.

Findings: 6 kg mass displacing left kidney and transverse colon into the right abdomen, compressing the IVC and celiac axis.

Protocol: Stepwise early inflow occlusion of the splenic artery at the superior border of the pancreas; careful hilar dissection; intact excision without capsular rupture.

Outcome: Rapid normalization of blood counts, functional recovery, and discharge without hemorrhagic or thrombotic events.

Media coverage of surgical resection of 6 kg giant splenic tumor by Dr. Ashok Kumar at SN Medical College
Press Coverage: SN Medical College 6 kg Splenic Extirpation
Case 09 Hypopharynx / Cervical Esophagus

Emergent Transcervical Excision of Obstructing 10 cm Polypoid Mass

Presentation: 40-year-old male with chronic dysphagia whose post-endoscopy retching provoked exteriorization of a 10 cm cylindrical mass from the mouth, causing acute asphyxiation risk.

Management: Emergency anterior cervical exploration within 20 minutes of arrival; complete base excision and multilayer mucosal repair.

Outcome: Immediate restoration of airway and esophageal continuity; histology revealed benign fibrovascular polyp; uneventful recovery.

Press coverage of emergency esophageal tumor removal and asphyxiation relief by Dr. Ashok Kumar at RMLIMS Lucknow
Press Coverage: RMLIMS Emergency Esophageal Tumor Resection
Case 10 Pancreas, Duodenum, CBD

Totally Laparoscopic Pancreaticoduodenectomy (Whipple Procedure)

Presentation: 64-year-old male with painless progressive jaundice and anorexia due to a periampullary neoplasm.

Procedure: Totally laparoscopic en-bloc resection of pancreatic head, uncinate process, duodenum, and common bile duct; performance of three intracorporeal anastomoses (duct-to-mucosa PJ, end-to-side HJ, and antecolic GJ).

Clinical Advantage: Sparing of standard 25 cm upper incision led to minimal blood loss, minimal surgical site morbidity, and accelerated functional recovery.

Newspaper report on totally laparoscopic Whipple surgery for pancreatic cancer by Dr. Ashok Kumar at SGPGI Lucknow
Press Coverage: SGPGI Minimally Invasive Whipple Resection
Case 11 Esophagus & Gastric Conduit

Thoracolaparoscopic McKeown Esophagectomy in a Hostile Abdomen

Background: 30-year-old male with previous pancreaticojejunostomy presented with esophageal cancer. Prior surgery interrupted standard right gastroepiploic arcade perfusion.

Surgical Strategy: Three-stage McKeown esophagectomy; creation of a non-conventional gastric conduit nourished solely by the right gastric artery (confirmed via fluorescein dye assessment); tension-free cervical anastomosis.

Outcome: Avoided complex colonic interposition; clear R0 margins and successful preservation of normal enteral nutrition.

Media press clipping on McKeown esophagectomy for foodpipe cancer in a hostile abdomen by Dr. Ashok Kumar at SGPGI
Press Coverage: SGPGI Thoracolaparoscopic McKeown Esophagectomy
Case 12 Gastric Body & Antrum

Laparoscopic Subtotal Gastrectomy with Radical D2 Lymphadenectomy

Presentation: 49-year-old male with antral gastric adenocarcinoma and profound early satiety.

Procedure: 75% distal subtotal gastrectomy; formal D2 lymphadenectomy dissecting perigastric (stations 1–6) and celiac/hepatic/splenic basins (stations 7, 8a, 9, 11p, 12a); endostapler reconstruction.

Outcome: Completed in 2 hours with minimal blood loss; accelerated return of peristalsis and early discharge.

Press article covering laparoscopic subtotal gastrectomy and D2 lymphadenectomy for stomach cancer by Dr. Ashok Kumar at SGPGI
Press Coverage: SGPGI Minimally Invasive Stomach Cancer Gastrectomy
Case 13 Left Colon & Prior Biliary Limbs

Complex Tertiary Abdominal Re-exploration for Metachronous Malignancies

Oncological Background: 49-year-old male with Lynch-spectrum syndrome and 14-year history of surgeries (Whipple in 2009, Right Hemicolectomy in 2013) presenting with anemia (Hb: 5 g/dL) from a third primary left colon cancer.

Procedure: 7-hour tertiary re-exploration through dense adhesions; radical left colectomy with en-bloc resection and revision of previously constructed biliary-enteric limbs involved by tumor.

Outcome: Microscopic R0 clearance; uncomplicated recovery; initiated on adjuvant systemic therapy.

Newspaper report on complex tertiary abdominal re-exploration for recurrent metachronous GI cancer by Dr. Ashok Kumar at SGPGI
Press Coverage: SGPGI Complex Recurrent GI Cancer Salvage
Case 14 Left Hepatic Lobe & Bile Duct

Laparoscopic Major Left Hepatectomy with Biliary Reconstruction

Presentation: 27-year-old male with profound jaundice (serum bilirubin: 24 mg/dL) due to left intrahepatic cholangiocarcinoma, optimized via preoperative PTBD drainage.

Procedure: Totally laparoscopic anatomical left hepatectomy (Segments II, III, IV) with vascular stapler control of left inflow branches; limited-incision Roux-en-Y hepaticojejunostomy.

Outcome: Negligible blood loss over a 12-hour surgery; 24h ICU observation; enteral intake resumed on POD 3 without biliary leak or liver failure.

Press clipping documenting major laparoscopic anatomical left hepatectomy and biliary reconstruction by Dr. Ashok Kumar at SGPGI Lucknow
Press Coverage: SGPGI Laparoscopic Major Liver Hepatectomy
Case 15 Retroperitoneum & Great Vessels

Laparoscopic Excision of a Recurrent Retroperitoneal Tumor

Presentation: 32-year-old female with recurrent 15 × 10 cm retroperitoneal tumor abutting the left ureter, mesenteric vessels, and aorta, three years post open excision.

Surgical Technique: Laparoscopic dissection through severe retroperitoneal fibrosis; skeletonization and preservation of the left ureter; complete en-bloc resection using ultrasonic energy.

Outcome: Operative duration 1 hr 40 min; zero wound morbidity; intact urinary function; discharged on POD 3.

Media press article reporting laparoscopic excision of recurrent retroperitoneal tumor sparing ureter and vessels by Dr. Ashok Kumar at SGPGI
Press Coverage: SGPGI Laparoscopic Recurrent Retroperitoneal Tumor Resection
Compliance Notice

Patient Disclaimer

These clinical case summaries and media clippings are published exclusively for medical education, clinical peer review, and academic informational purposes. Clinical outcomes and surgical interventions are specific to individual disease presentation and do not constitute a guarantee of results.